Kategorien

An inflatable medical tent creates temporary covered space for triage, waiting, staff support, equipment, or field-health tasks. With 20 years of experience as a direct medical tent manufacturer, we supply field hospital tents, medical shelter tents, and mobile clinic units for disaster response and emergency medical care worldwide.

It solves a space and deployment problem — but it does NOT automatically provide negative pressure, sterility, infection control, or clinical capability. Common medical tent dimensions: 12m² triage units to 40m² field hospitals, with 2.4–3m ceiling height for equipment clearance.
Short answer: Use a portable medical tent or mobile clinic tent when you need a movable medical-support space with a clear internal task. Define who enters, what happens inside, what equipment is used, and which utilities are available — before choosing the shelter. Medical tent prices start at $1,200 for a basic 12m² unit and go up to $6,000+ for complete field hospital systems.

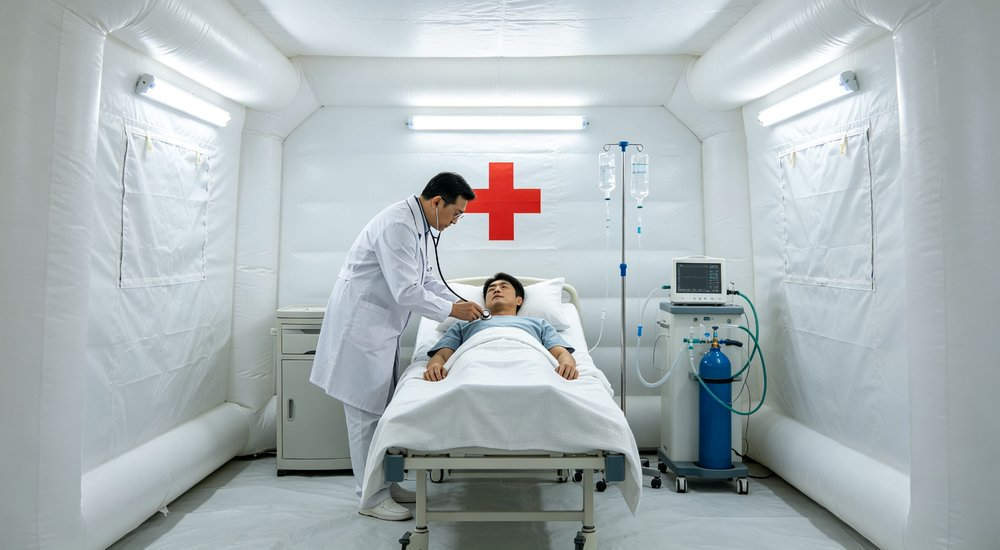
Medical tents require 6-12 air changes per hour for general areas and 12+ for treatment zones. HVAC options include portable AC units, forced air heaters, and exhaust fans. Confirm ducting connections, power requirements (typically 3-5 kW per unit), and temperature control range (-20°C to +50°C) before purchase.
Flooring options include integrated PVC ground sheets, removable foam mats, and raised wooden floors for wet terrain. Lighting typically uses LED strip lights (12V or 220V) with dimmers. Some models include pre-installed lighting circuits; others require separate lighting kits.
A 12m² medical tent holds 4-6 beds or serves as a triage station. A 30m² unit accommodates 10-15 beds plus staff workspace, equipment storage, and a waiting area. Modular systems can be connected to create full field hospitals with separate zones.
Most medical tents need a 5-10 kW generator for lighting, HVAC, and equipment. Oxygen supply can be via portable cylinders or concentrators — confirm tent has pass-through ports for tubing. Waste management requires sealed bins and designated disposal areas per local health regulations.
Accessibility note: medical tents can be configured with ADA accessibility features including ramps, wide entrances (minimum 90cm clear width), and accessible patient bays. Confirm these options with the manufacturer during the quote phase.
Buyers often search for these related terms: mobile field hospital. Understanding these variations helps you match the right product to your operational requirements.
A fixed building or temporary healthcare facility may be unavailable, too small, too far, or unsuitable for a temporary task. An emergency medical tent adds separate covered space without treating it as permanent. A 20m² mobile medical tent typically supports 4–6 beds or 10–15 seated patients, with 1.2m minimum aisle width for stretcher access. including triage tent, emergency clinic, disaster medical response, and pandemic response tent applications.

The shelter may support triage, waiting, staff preparation, equipment protection, or another clearly defined function. Each task changes the layout, openings, floor, ventilation, lighting, and utility needs.
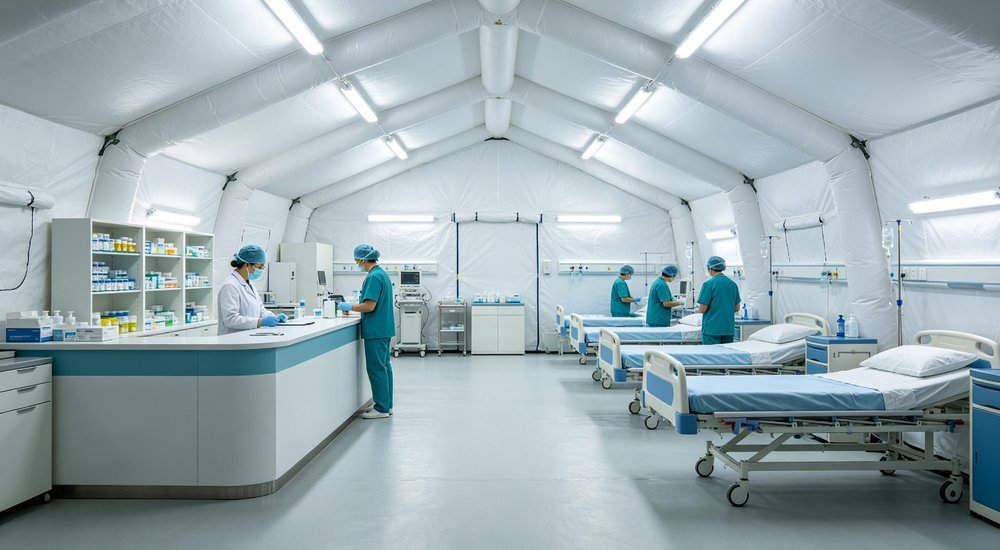
Name one primary task for each space. Combining waiting, treatment, storage, and staff rest without a layout creates cross-traffic, blocked access, and unclear cleaning responsibility.

Use a short task statement: name the users, activity, major equipment, expected occupancy, and connection to the next space. This makes configuration decisions traceable to real work.
Triage needs an obvious entry, a short assessment path, privacy where required, and a safe route onward. The tent gives a physical place for this work, but the medical process comes from your team. Medical tent ventilation should provide 6–12 air changes per hour (ACH) for general areas, with temperature maintained at 18–26°C.
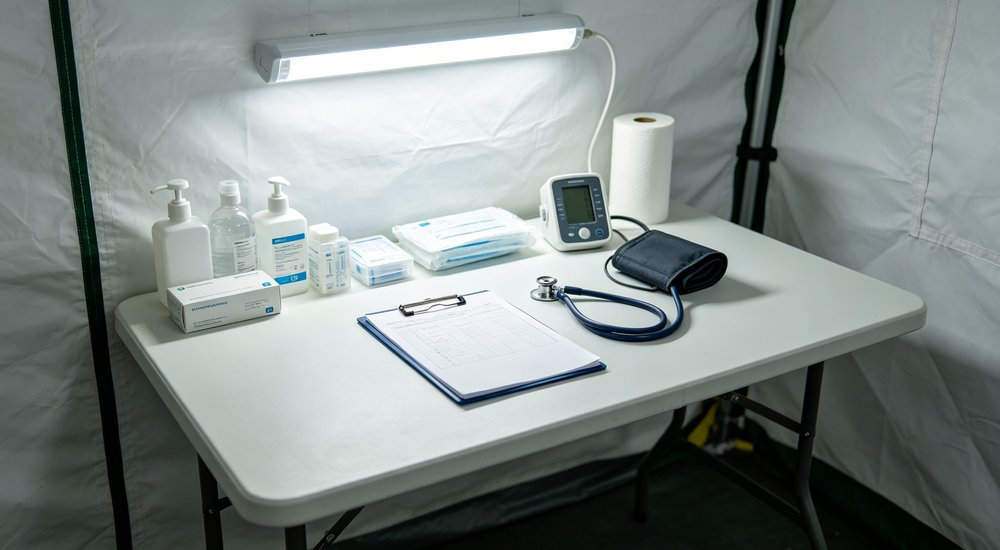
Start with expected arrivals, whether people walk or use stretchers, number of work positions, and next destination. These determine door width, turning space, internal zones, furniture, lighting, and staff movement.
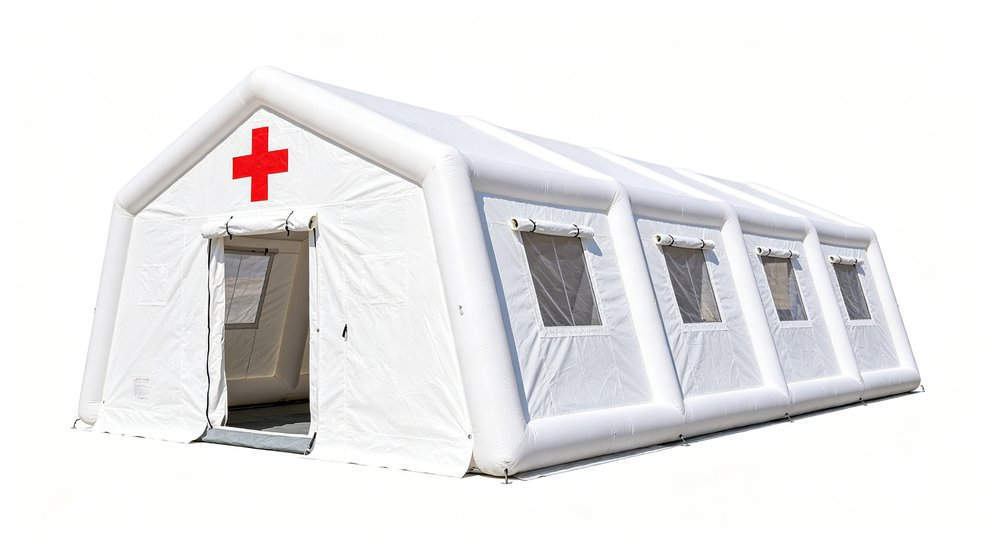
A tent large enough externally may still fail when air beams, desks, screens, and routes consume the interior. Ask for a marked layout using the proposed clear dimensions.
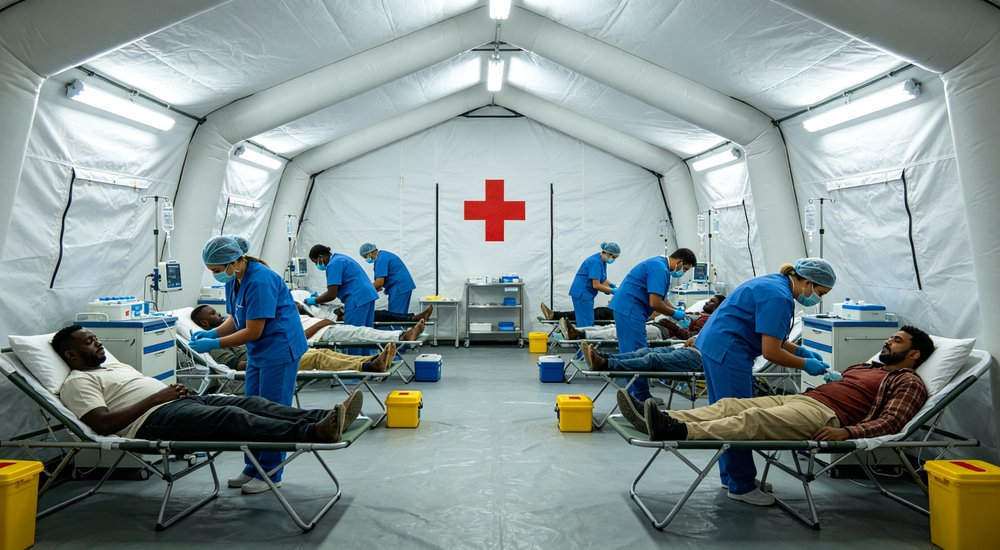
Standard medical tent fabric is flame-retardant 350–450g/m² PVC, with optional transparent window panels for natural light. Certifications to confirm: CE, ISO 9001, CPAI-84, NFPA 701.
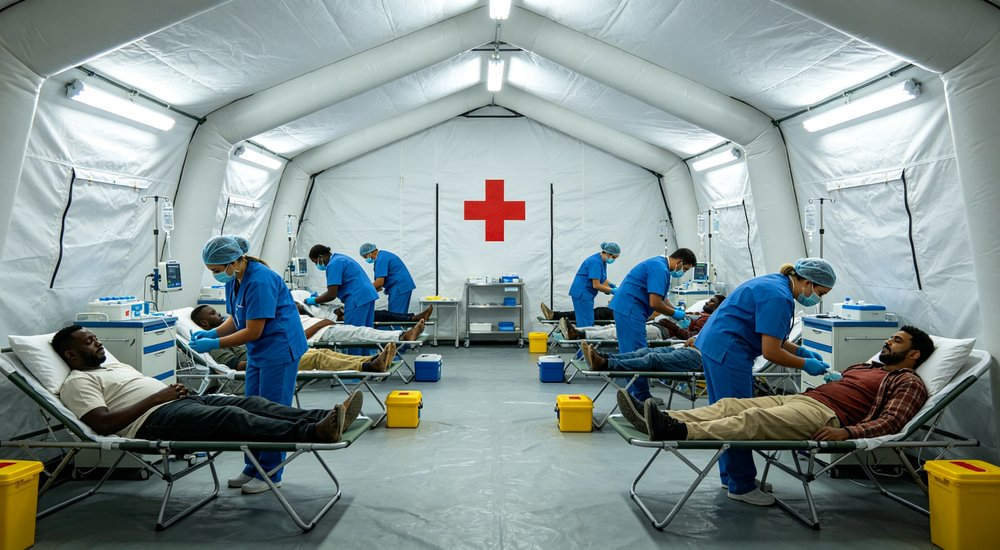
A dedicated waiting space keeps people away from assessment, treatment, staff, or equipment areas. This is useful when you need order and weather protection around a temporary medical point — common in disaster medical tent deployments and military medical tent operations.

The layout should show seated or standing occupants, entry and exit, accessible movement, staff observation, and clear space. Occupant count cannot be calculated from floor area alone.
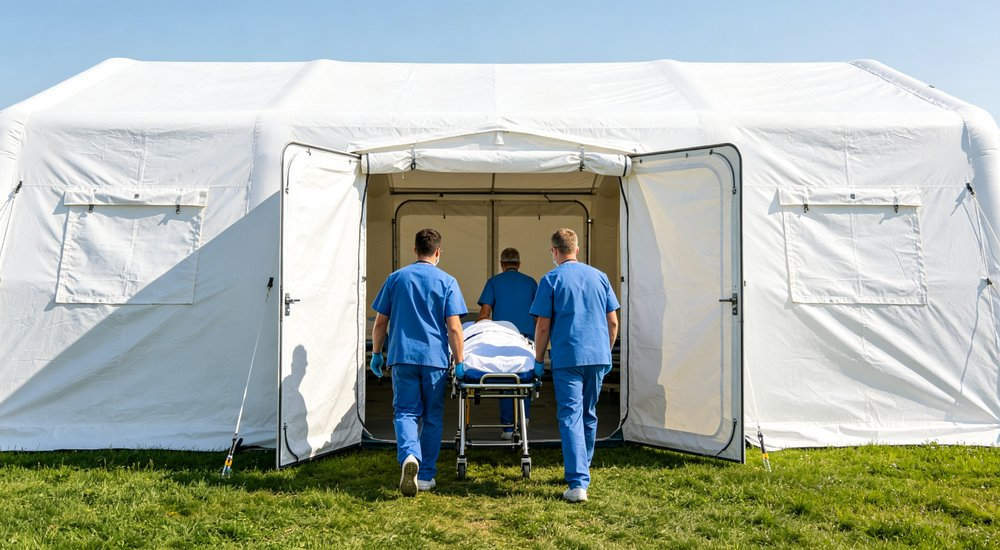
This does NOT prove infection-control separation. If you need controlled airflow or isolation, it requires a different system definition and validation — see how isolation tents differ.

Medical teams also need a covered area for preparation, records, briefings, changing, rest, or protected equipment. Separating these activities reduces interference with patient-facing work. See how to choose a medical tent for your site. Compare with frame tents for long-term camps, and understand why air-beam design matters.
Define desks, seating, lockers, charging, lighting, communications, cable routes, and access frequency. The shelter configuration should follow these items, not a general occupant estimate.
Covered space protects equipment from direct exposure and organizes its use. But you still need to define equipment size, weight, heat, power, ventilation, cleaning, and movement.

Power cables, air ducts, communication lines, and other connections need planned entry points. An improvised opening can affect weather protection, movement, and how the shelter closes.

The supplier response should identify available interfaces and what remains site-supplied. It should not assume a tent shell includes power distribution, medical tent HVAC, medical gases, or specialist equipment.
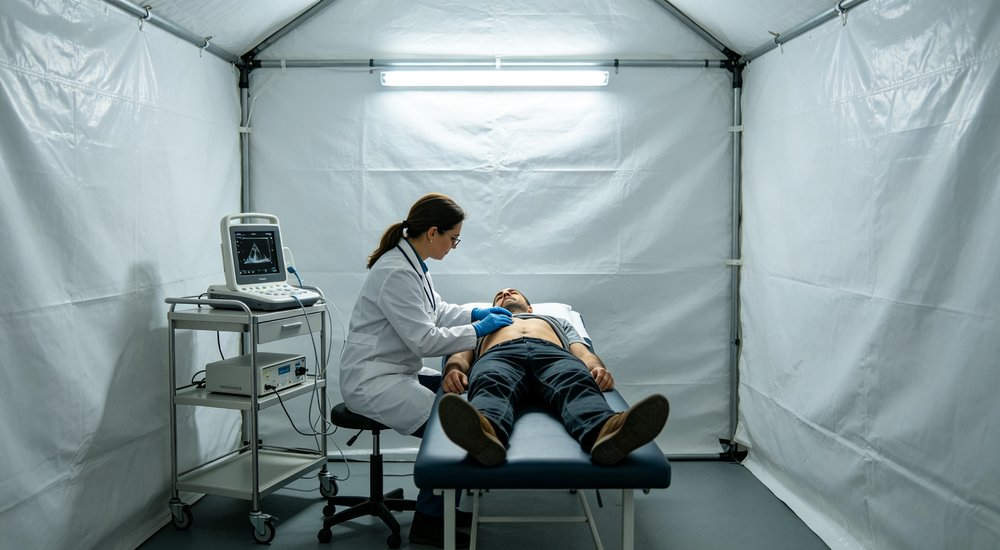
Request the position and clear size of every proposed interface. Check that cables or ducts do not cross an exit, block equipment, or prevent weather closure.
Medical use describes the work around the shelter. Isolation requires additional control of airflow, pressure differential, air changes, filtration, monitoring, alarms, and power.

A closed door, sealed-looking wall, fan, or filter does NOT prove negative pressure. The complete system needs a stated target, compatible components, an operating method, and applicable validation.

Choose a general medical-support configuration for space, access, and workflow needs. Choose an isolation direction only when you can define and support the required environmental controls.

|
Need |
Standard Medical Tent |
Isolation Tent (separate system) |
|
Covered space |
✅ Yes |
✅ Yes |
|
Triage / waiting / staff |
✅ Yes |
✅ Yes |
|
Negative pressure |
❌ No |
✅ With complete system |
|
HEPA filtration |
❌ No |
✅ Optional add-on |
|
Pressure monitoring |
❌ No |
✅ Required |
|
Price range |
$1,200–$3,500 |
$4,000–$6,000+ |
A project may work better with separate tents or connected modules for triage, waiting, staff, equipment, and isolation. Separation makes routes and responsibilities easier to understand. See when modular systems make sense.

Connected systems need compatible corridors, end walls, doors, partitions, and weather protection at each joint. There is no universal maximum layout.

Ask the supplier to show the proposed arrangement and every connection component. The layout should also explain what happens if one module is removed or used independently.
Movement between modules needs the same attention as movement inside them. Corridors and doors should fit the people, stretchers, carts, and equipment that actually pass through.

A groundsheet or medical tent flooring separates the interior from dirt and limited surface moisture. It cannot repair a low site, poor drainage, standing water, or inadequate ground support.

Medical tasks may require different cleaning methods for waiting, staff, equipment, or patient-facing spaces. State the intended cleaning method and any substances that contact the floor or cover.

The supplier should explain the floor connection, edges, joints, cleaning direction, and replacement scope. Do not infer chemical resistance or hygiene performance without applicable product evidence.

Separate cleaning the tent from preparing the site. Drainage, levelling, protective layers, waste handling, and access may remain your responsibilities.
Air beams reduce rigid frame components, but the project depends on pumps, valves, chamber arrangement, pressure retention, and repair capability. These affect how the shelter is checked before occupancy and maintained during use.

Ask which chambers are independent, how pressure change is identified, and what area one problem may affect. Request the matching pump, valve information, repair materials, and post-repair checking method. See why air-beam design matters.

Do not copy pressure values, chamber counts, or repair claims from another model. A medical-support plan needs answers tied to the shelter actually offered.
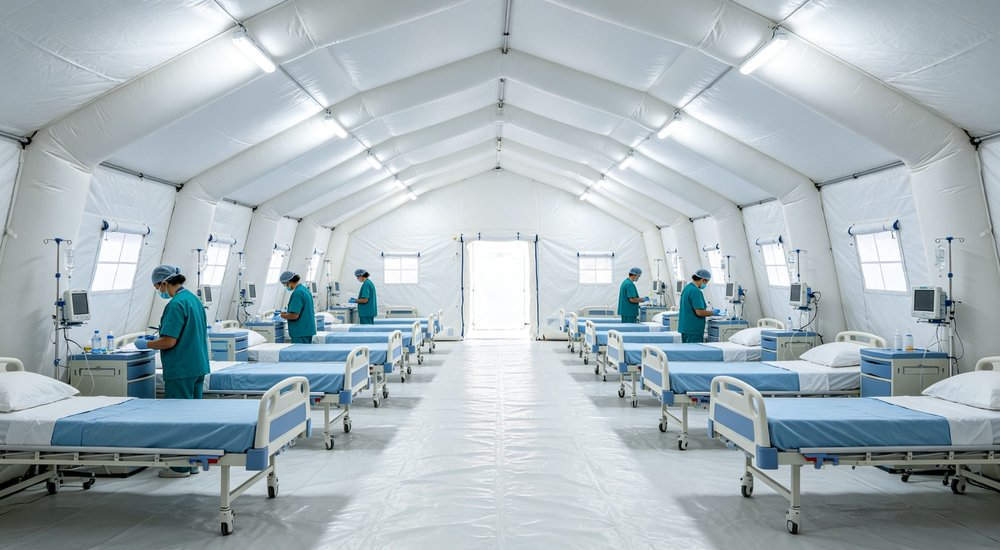
The continuity plan should describe the response to pressure change during occupancy: move users, isolate a chamber, apply temporary repair, or replace a component. The correct action depends on the offered structure.
Grass, soil, sand, pavement, and indoor floors need different anchoring and floor treatment. State whether stakes are permitted and whether ballast or other site work is available.

Expected wind, rain, temperature, drainage, operating duration, and nearby exposure affect the choice. Any environmental rating must belong to the current configuration and available documents.

The site also needs room for entrances, equipment, service lines, anchoring, and safe movement around the shelter. External dimensions alone do not show the complete site footprint.

Request a site footprint that includes guy lines, ballast, service equipment, and access routes. Compare it with the available area and obstacles.
Project A — Triage near existing facility: Power and medical equipment already exist. The shelter decision focuses on access, zones, clear space, lighting interfaces, floor, and anchoring. Budget: $1,200–$2,500. Our medical tent supplier program offers CE certified factory price and wholesale medical tents for bulk procurement.

Project B — Isolation at remote site: Must define pressure, air changes, filtration, monitoring, alarms, backup power, and validation. A general medical tent cannot close these requirements alone. Budget: $4,000–$6,000+.

Both may use inflatable structures, but they should not receive the same offer. Defining the task prevents a basic space from being oversold and a specialist system from being under-specified.
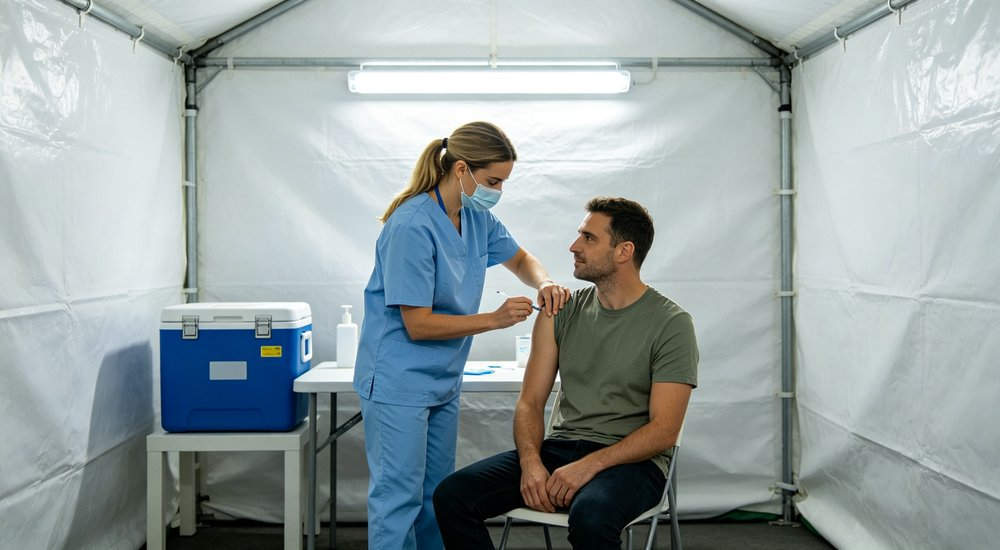
Send: primary task, users, expected flow, equipment, internal layout, site, ground, weather, duration, quantity, utilities, and required medical-support systems. State which fields are fixed and which remain ranges.

The supplier should return: clear internal dimensions, air-beam and chamber direction, openings, zones, floor, anchoring, included medical tent accessories, optional systems, packing, and available documents. Confirm the full accessory scope.
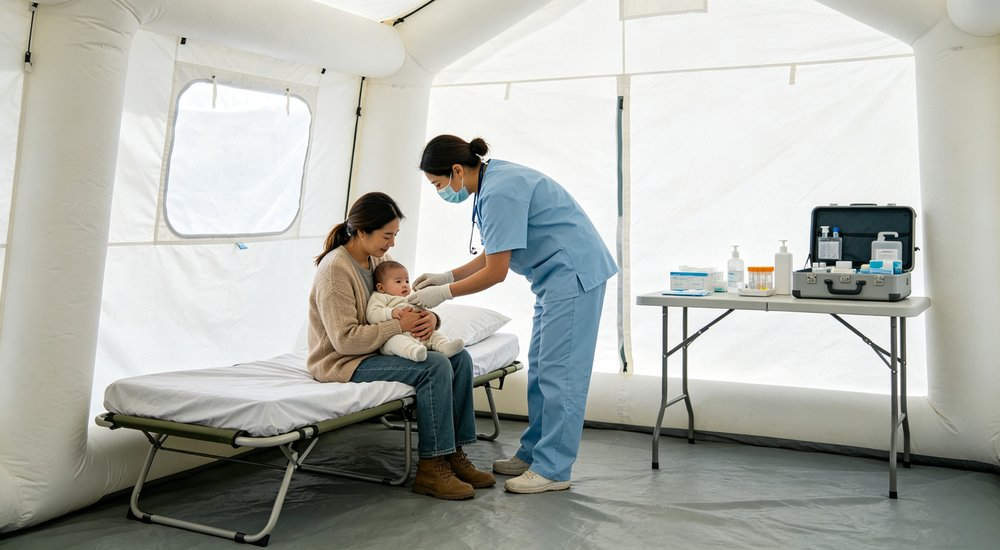
The response should separate the basic shelter from furniture, utilities, medical equipment, and site work. For each optional system, name its function, interface, service need, and document scope.
MOQ & lead time: Standard models: MOQ 1–10 units, lead time 15–30 days. Custom colors/logos/systems: MOQ 50+, lead time 30–45 days. Confirm these before ordering.
Medical tent prices range from $1,200 for a basic 12m² triage unit to $6,000+ for a 30–40m² field hospital system with HVAC, partitions, and medical interfaces. Always compare complete sets, not just the tent shell.

A 12–20m² rapid deployment medical tent takes 15–30 minutes with 2–3 people using an electric pump. Larger systems need 4–6 people and 30–60 minutes. Times exclude equipment setup and anchoring.

Not automatically. "Medical tent" describes an intended support use, but regulatory status depends on the exact product, complete system, claims, market, and applicable documents. Define your intended function and ask which documents apply.

Only when the complete configuration and project controls support the intended treatment task. The shelter shell provides space, cover, openings, flooring, and interfaces — it does not provide clinical equipment, staffing, or treatment protocols by itself.

No. Medical tent HVAC may be optional, supplied separately, or outside the shelter offer. Its selection depends on climate, occupancy, equipment heat, airflow needs, power, and operating duration.
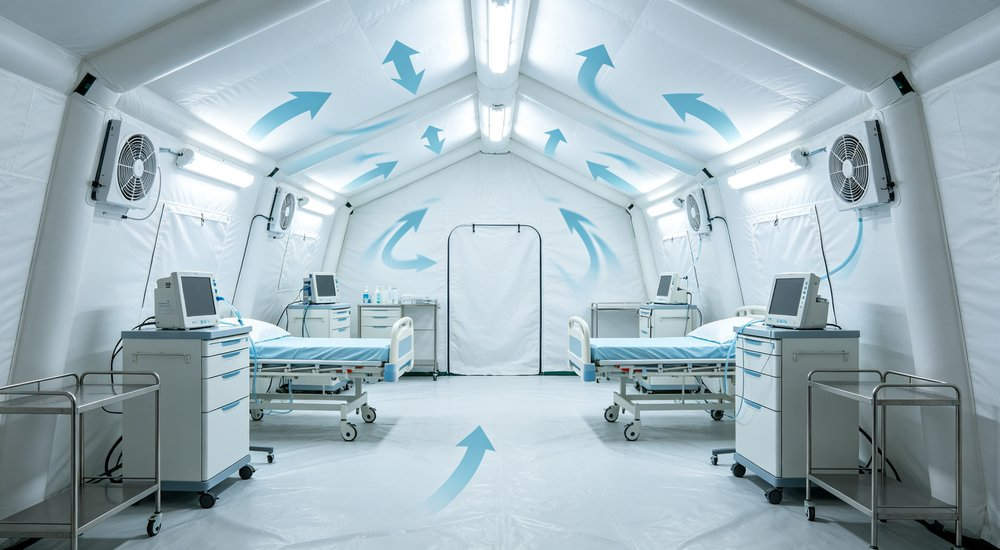
No, unless the offered complete system explicitly includes and supports it. Negative pressure needs target pressure differential, airflow, filtration, monitoring, alarms, power, and validation. A closed shelter, fan, or filter is not enough.
Only when the proposed openings, routes, turning space, floor transitions, and internal equipment allow it. Provide stretcher dimensions and ask for a marked layout with clear door width and movement routes.
It depends on ground, drainage, loads, movement, cleaning, and the exact task. A groundsheet may separate from dirt and limited moisture; a more stable floor better supports carts or equipment. Neither corrects a poor site or standing water.
Some configurations use corridors, connector kits, or modules, but connection is not universal. Compatibility depends on the exact structure, opening, height, weather seal, and floor. Ask for a complete layout drawing and every connection component.
Standard models: MOQ 1–10 units, lead time 15–30 days. Custom colors, logos, or specialist systems: MOQ 50+ units, lead time 30–45 days. Confirm with the supplier before finalizing.

 |

|
Freundliche Links :
Urheberrechte © © Custom Disaster - Relief Bedding: Tents, Sleeping Bags, Blankets Alle Rechte vorbehalten
das professionelle Team zum Service !


